Medically reviewed by Dr. Meir Tako, DC, CCSP · Updated
Tension headaches and cervicogenic headaches, which start in the neck, are among the most common types of headache. Chiropractic care can help when muscle tension or stiff joints in the neck and upper back are contributing. The first step is an evaluation to understand your headache pattern and rule out signs that need a medical doctor.
What kind of headaches can a chiropractor help with?
Headaches have many causes, and they aren’t all the same condition. The two types most often linked to the neck and upper back are tension headaches and cervicogenic headaches.
Tension headaches are the most common type. They usually feel like a dull, pressing band around the forehead, temples or the back of the head. They’re often linked to tight muscles in the neck, shoulders and scalp, and to stress, poor sleep and long hours in one position.
Cervicogenic headaches start in the neck itself. Irritated joints, muscles or nerves in the upper neck refer pain into the head, often on one side, starting at the base of the skull and spreading toward the eye or temple.
Migraines are a different, neurological condition. They should be diagnosed and managed with your physician or a neurologist. Some people with migraines also have neck and shoulder tension that seems to act as a trigger, and addressing that may help as part of a broader plan. Chiropractic care is not a replacement for medical migraine care.
Common symptoms
- A dull, pressing or tight feeling around the head, like a band
- Pain that starts at the base of the skull and spreads to the temple, forehead or behind the eye
- Headaches mostly on one side, often the same side each time
- Neck stiffness or reduced range of motion along with the headache
- Headaches that build through the afternoon, especially on workdays
- Headaches triggered by certain neck positions, long screen time or poor sleep
Keeping a simple headache diary (when it starts, where it hurts, what you were doing) is one of the most useful things you can bring to your first visit.
What causes it?
Common causes and contributors to tension and neck-related headaches include:
- Stiff joints in the upper neck. The top three vertebrae share nerve pathways with the head, so irritation there can be felt as headache.
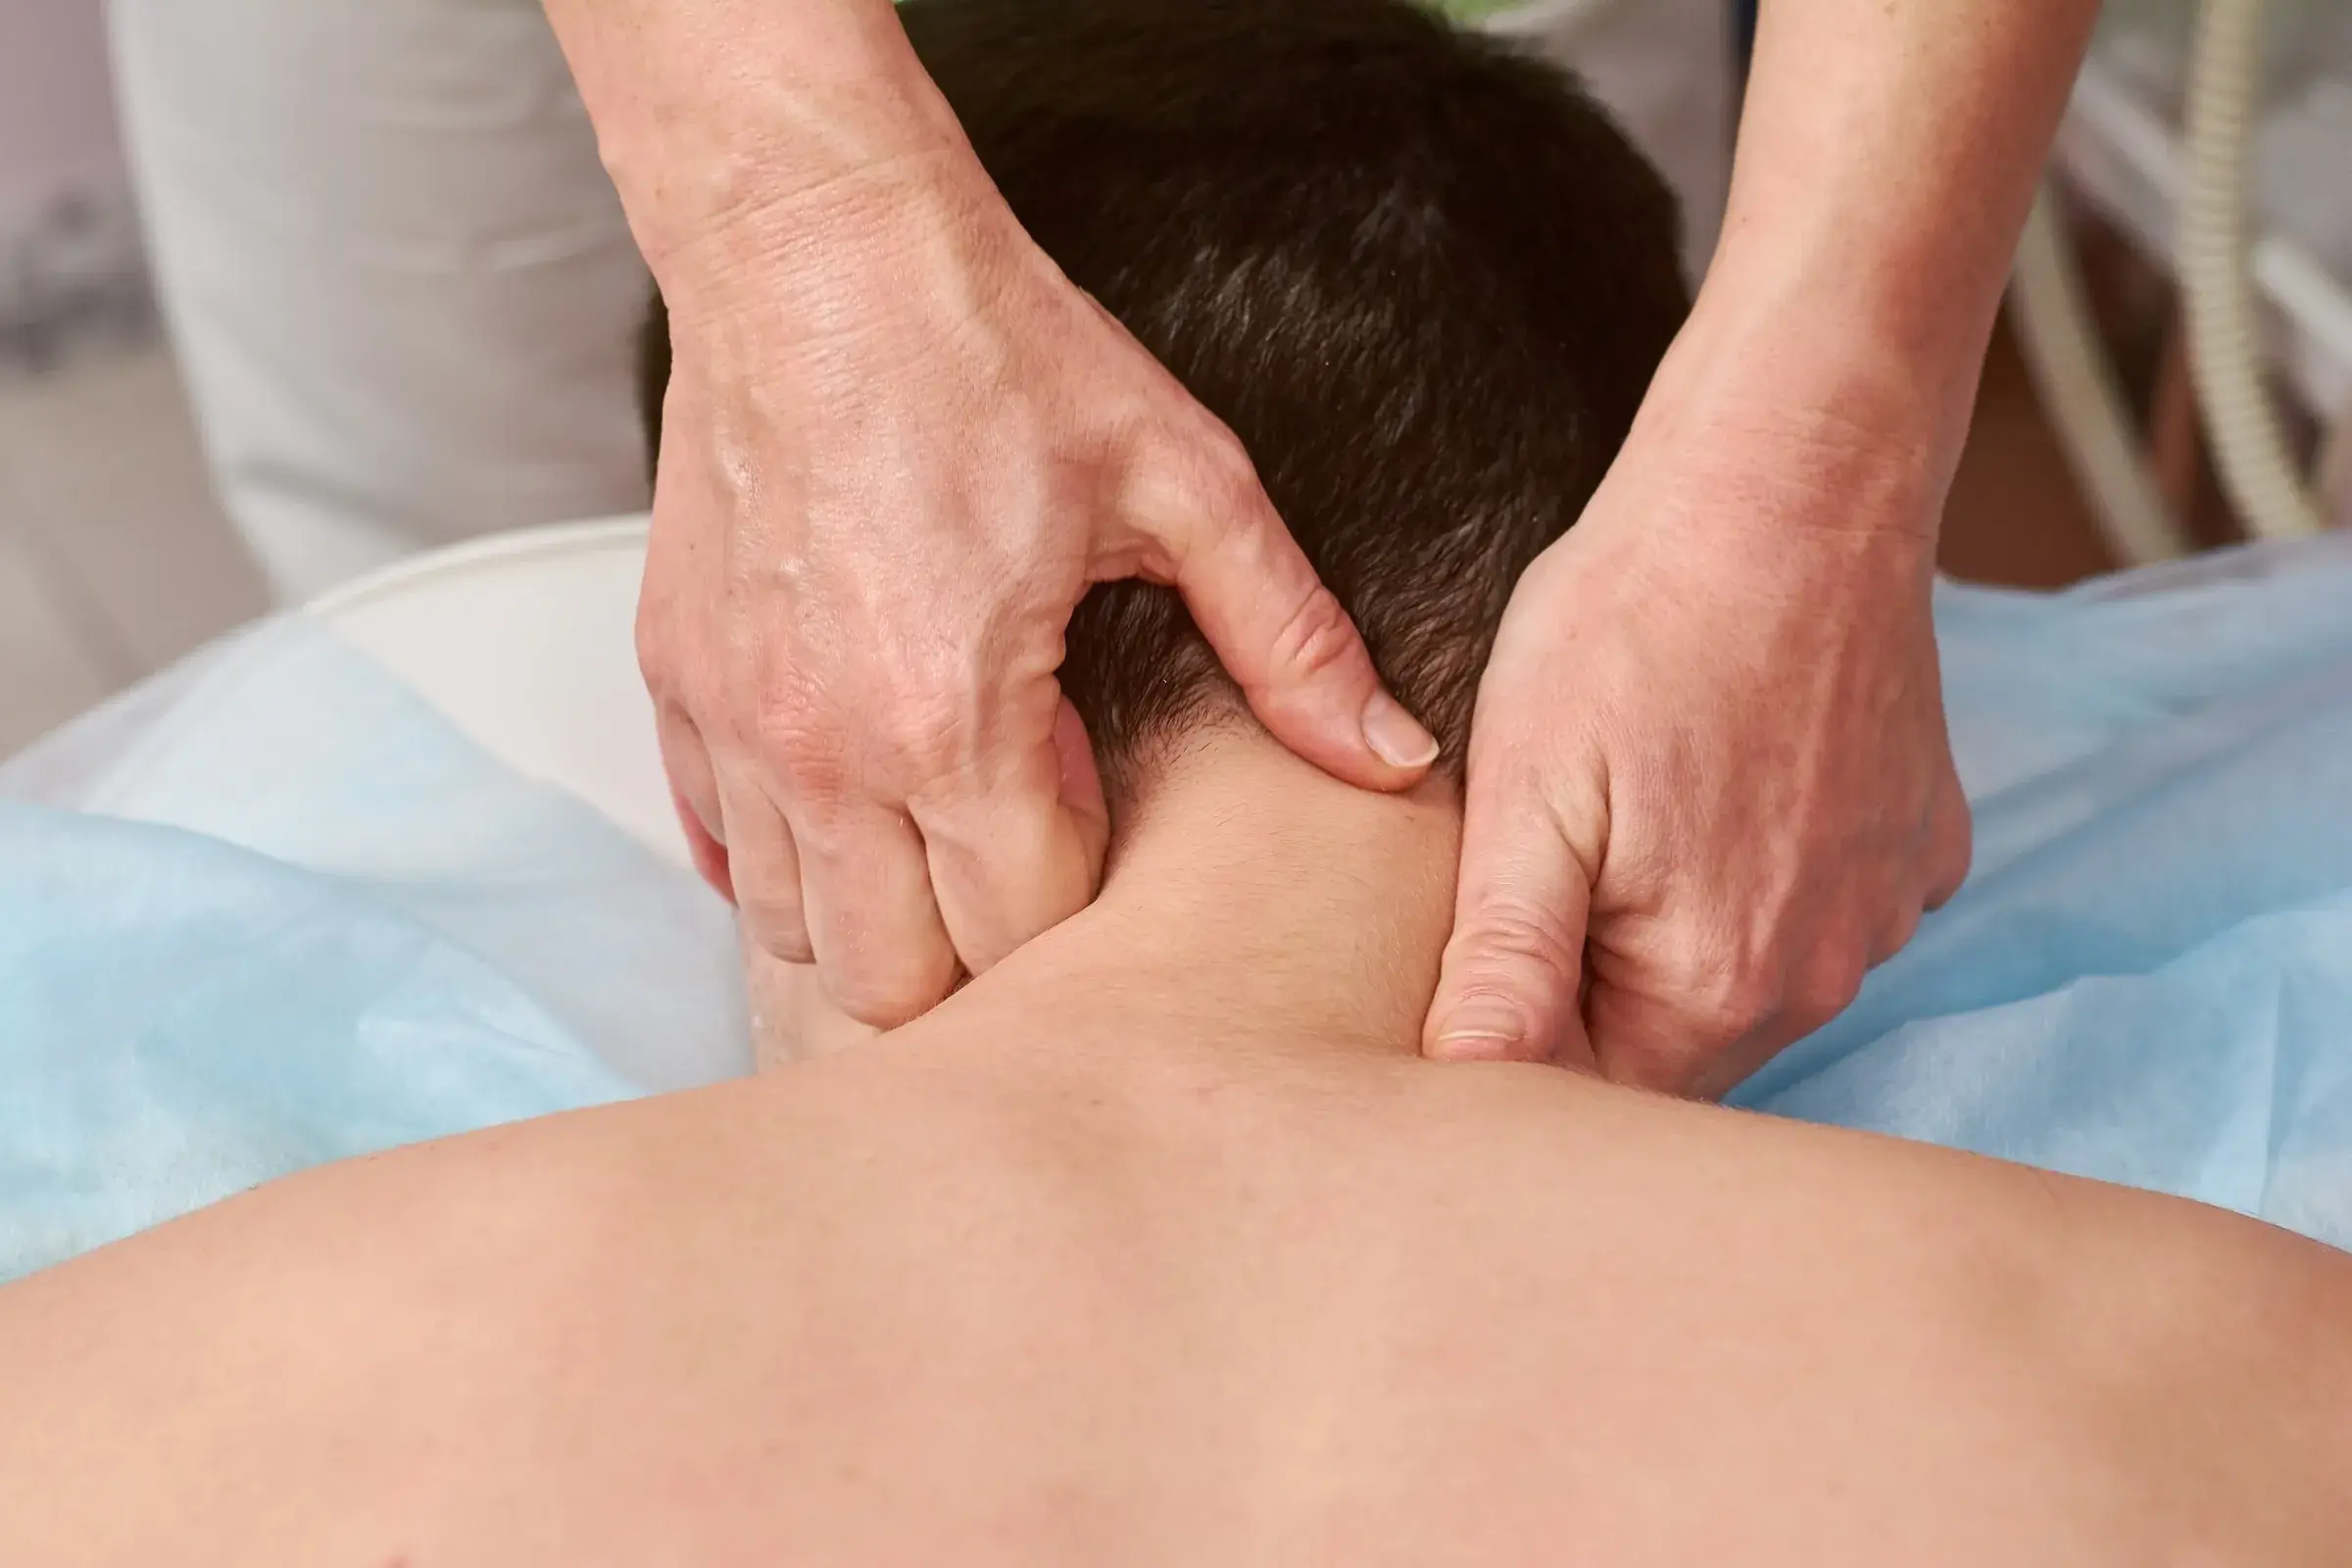
- Muscle tension in the neck, shoulders and jaw. Tight muscles at the base of the skull and across the shoulders can refer pain into the head.
- Sustained postures. Hours with the head pushed forward toward a screen load the upper neck and the muscles that hold it.
- Jaw clenching and TMJ problems. Grinding or clenching, especially at night, can feed headaches at the temples and around the ears.
- Stress, sleep and dehydration. These don’t cause neck problems on their own, but they lower your threshold and make headaches more likely.
- Old injuries and compensations. A past whiplash, a concussion that has since been cleared, or even a shoulder injury can change how the neck moves and leave it holding tension for years.
How Dr. Tako finds the source
Headaches are a symptom, so the first job is understanding the pattern: when they happen, where they start, what makes them better or worse, and whether anything in your history needs a medical doctor first.
Consider a common example. A patient has right-sided headaches three afternoons a week. Pain medication helps, but the headaches keep coming back. The exam shows the upper neck barely rotates to the right, and the right jaw muscle is tender. The patient also clenches at night. In this case the headache is the end result of a jaw and upper-neck pattern. Treating only the head would miss it.
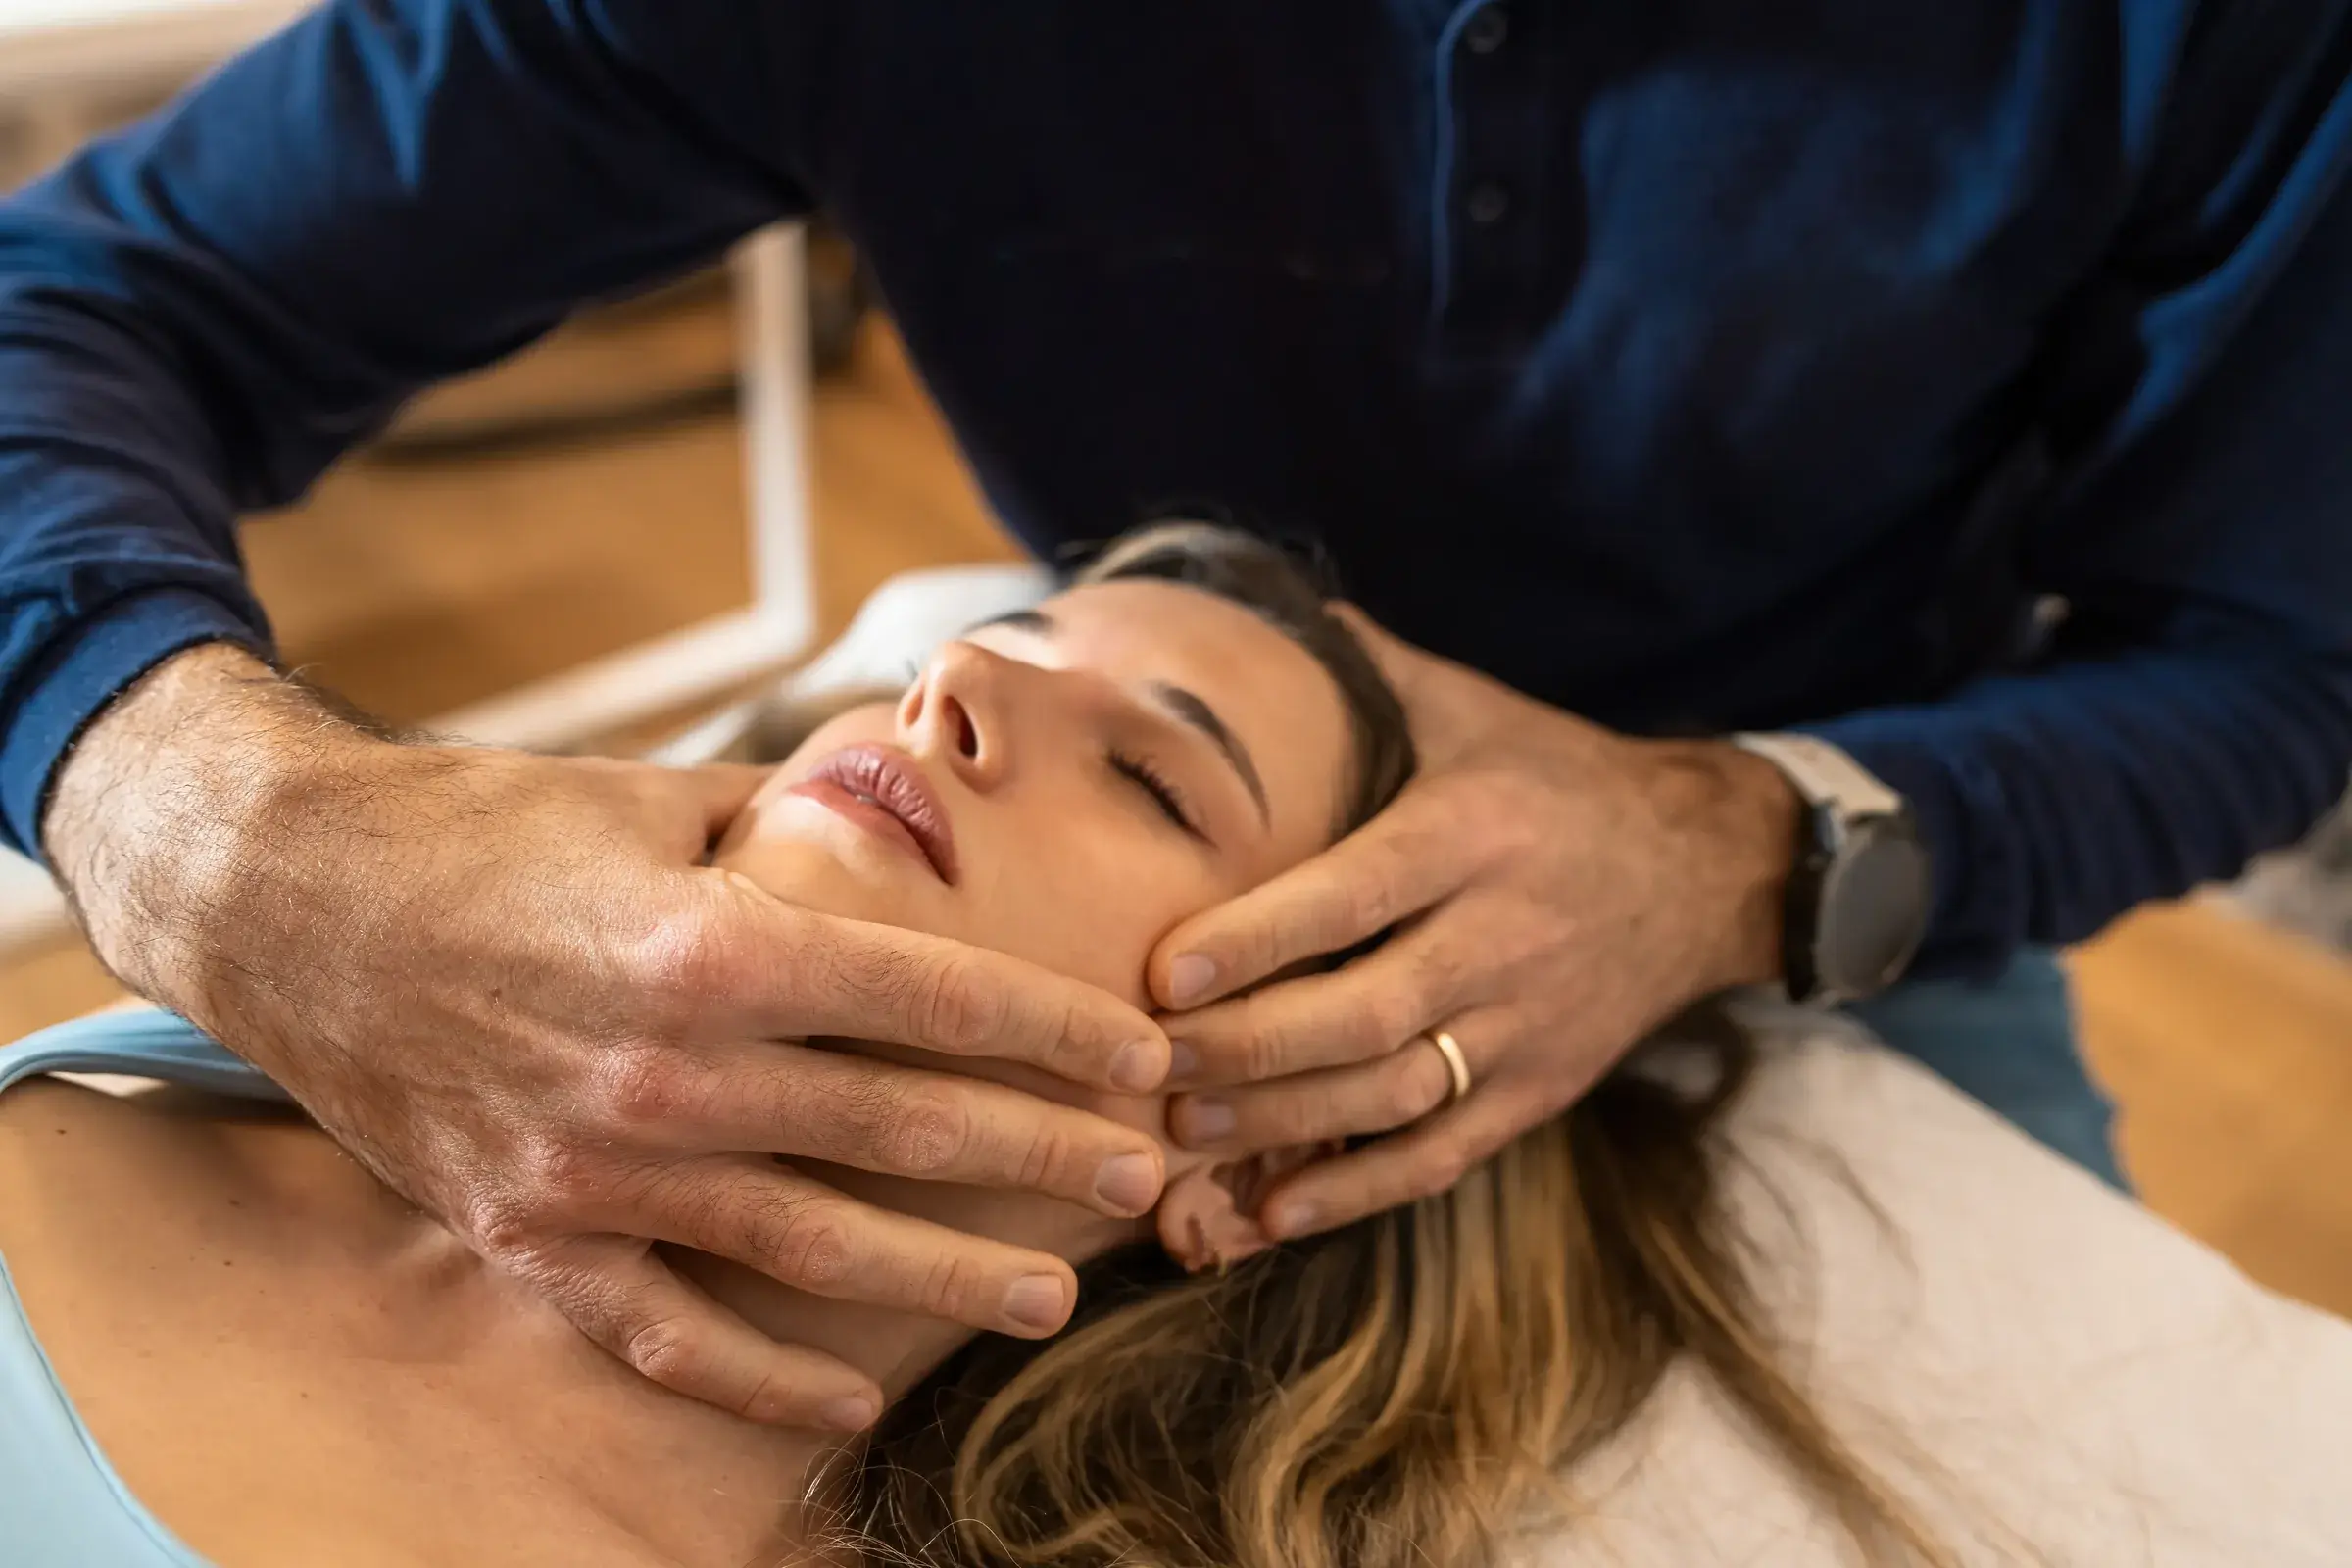
The evaluation typically includes your history (including past head and neck injuries), posture and movement, joint testing of the neck, upper back and jaw, and muscle strength testing. Dr. Tako also uses P-DTR, a functional neurology method that uses muscle testing and stimulation of specific sensory receptors to find protective patterns in the nervous system. These patterns can keep neck and jaw muscles tight long after the original strain has settled.
Treatment is matched to what he finds. It may include gentle adjustments to the neck and upper back using Gonstead, Activator or drop table techniques, soft tissue work for the neck, shoulders and jaw, and practical changes to your desk setup and daily routine.
The goal is a clear answer to three questions: what type of headache you have, what is driving it, and what will help keep it from coming back.
Headaches in desk workers and screen-heavy jobs
If your headaches show up most on workdays, especially in the afternoon, your workstation is worth a close look. Long hours of focused screen work tend to bring the head forward and the shoulders up, and many people hold their breath or clench their jaw without noticing. The upper neck and the muscles at the base of the skull take most of that load.
Part of your plan covers the habits that keep headaches coming: screen height and distance, how often you move, how you sleep, and short exercises for the neck and upper back that fit into a workday. Many patients notice that small changes, combined with treatment, make the biggest difference.
If you rely on pain medication most days of the week, talk to your physician. Frequent use of headache medication can itself contribute to ongoing headaches, and that’s worth sorting out alongside your care here.
When to seek urgent care instead
Call 911 or go to the emergency room for a sudden, severe headache that feels like the worst headache of your life, or a headache with weakness, numbness, confusion, trouble speaking, vision loss or a seizure. A headache with fever and a stiff neck, or any headache after a head injury, also needs urgent medical care. See a medical doctor first for new headaches after age 50, headaches that are steadily getting worse or changing pattern, or headaches that wake you from sleep.
This page is for education and isn't a substitute for a medical diagnosis. Individual results vary.